A Wake–Up Call for Congress on Mental–Health Reform – guest commentary
(Mar. 30, 2016) Another shooting at the U.S. Capitol. This time, in an incident on Monday, 66-year-old Larry Dawson, a Tennessee man known to U.S. Capitol Police for his erratic behavior, was shot and wounded by a police officer when he pulled out what sources later said was a pistol-like pellet gun.
 What is going on? One possible answer was offered earlier this month by 30-year-old Kyle Odom, who was arrested March 8 after throwing a letter to President Obama over the White House fence. The letter warned the president that there are at least 50 members of Congress, both Republicans and Democrats, who are Martians. Then, in a 21-page manifesto released to the media, Mr. Odom provided the names of these congressional Martians and described how they live “deep underground here and inside the moon.” Law-enforcement officials say that two days before the White House incident, Mr. Odom shot and critically wounded an Idaho minister, believing that the clergyman also was a Martian.
Kyle Odom had not always believed in extraterrestrials. He served four years as a decorated Marine, graduated from the University of Idaho with honors, and was accepted into a prestigious Ph.D. program in genetics. Then he developed delusions and auditory hallucinations, classic symptoms of schizophrenia. Like many with this disease, though, he apparently has had no awareness of his own illness.
Mr. Odom joins a long line of individuals with untreated mental illness who have come to the attention of Congress. In 1998 Russell Weston, with untreated schizophrenia, shot his way into the Capitol building, killing two guards before finally being stopped as he entered the office of then-House Majority Whip Tom DeLay. In response, Congress vowed to do something about untreated mental illness but did nothing.
In 2011 Jared Loughner, with untreated schizophrenia, severely wounded then-Rep. Gabrielle Giffords in Tucson, Ariz., and killed six others. In response, Congress vowed to do something but did nothing. Then in 2013 Miriam Carey, seriously mentally ill, was killed by U.S. Capitol Police on the Capitol grounds, causing a lockdown of the building. During these same years there have been at least 20 widely publicized mass shootings by individuals with serious mental illness that was not being treated.
Mr. Odom’s arrival in Washington with his list of Martian members of Congress has come at a time when there are multiple legislative proposals, in both the House and Senate, to improve the nation’s broken mental-illness treatment system. The strongest bill is from Rep. Tim Murphy (R., Pa.), the Helping Families in Mental Health Crisis Act (H.R. 2646), which has 135 Republican and 51 Democratic co-sponsors. It is the only proposal that would be likely to affect the actual treatment of Kyle Odom, Miriam Carey, Jared Loughner, Russell Weston and other individuals with untreated serious mental illness who, because of the effect of the disease on their brain, are unaware of their own illness and need for treatment.
Kyle Odom said it best at the beginning of his manifesto: “As you can see, I’m pretty smart. I’m also 100 percent sane, 0 percent crazy.” The provision in Rep. Murphy’s bill, which would make treatment possible, is called assisted outpatient treatment (AOT) and requires the individual to follow a court-ordered treatment plan. In study after study, AOT has been shown to significantly reduce hospitalization, incarcerations and violent acts among individuals with serious mental illness.
There may not be any Martians in Congress, despite Kyle Odom’s claims, but if lawmakers continue to thwart this common-sense reform of mental-health policy, voters could begin to suspect that Mrs. Pelosi and her colleagues live on another planet.
E. FULLER TORREY, M.D.
FOUNDER, TREATMENT ADVOCACY CENTER
Read the entire column here.
To comment, visit our Facebook page.
Visit our blog archive to read all our recent posts.
RESEARCH WEEKLY: What We Can Learn from Sweden
(March 29, 2016) Collecting and reporting national statistics for more than 100 years, Sweden's National Patient Register (NPR) is a virtual mother lode of statistical gold for health researchers.
For example, county governments in Sweden have been required to submit statistics on inpatient psychiatric care to the NPR since 1987 and on outpatient psychiatric treatment from both public and private caregivers since the early 2000s. Such a wealth of longitudinal data makes it possible to identify trends and patterns that might be undetectable in local data alone or in data collected over shorter periods.
Seena Fazel, MD, of the University of Oxford department of psychiatry in the United Kingdom, and Paul Lichtenstein, PhD, of the Karolinska Institutet in Sweden, have worked with a variety of collaborators to examine the NPR for associations between psychiatric disease and specific negative outcomes, including criminal violence. Following are three examples of their findings.
Medication and Violence
- "Antipsychotics, mood stabilisers, and risk of violent crime" (2006-2009)
Premise: The authors aimed to "establish the effect of antipsychotics and mood stabilisers on the rate of violent crime committed by patients with psychiatric disorders in Sweden."
Finding: Mentally ill individuals were substantially less likely to commit violent crimes when taking psychiatric medication. Among the estimated 83,000 Sweden patients prescribed antipsychotics or mood stabilizers during the study period, violent crime fell by 45% in patients who were receiving antipsychotic medications and 24% in patients with bipolar disorder who were prescribed mood stabilizers. Reductions in violence were greater in patients who were prescribed higher drug doses.
- "Depression and violence: A Swedish population study" (2001-2009)
Premise: The authors aimed "to determine the risks of violent crime in patients with depression and to investigate the association between depressive symptoms and violent crime in a cohort of twins."
Findings: Individuals with depression were significantly more likely to commit violent crimes than the general population even after discounting for factors such as substance abuse and prior violent conviction. When the additional risk factors were present, risk increased further.
- "Violent crime, suicide, and premature mortality in patients with schizophrenia and related disorders: a 38-year total population study in Sweden" (1972-2009)
Premise: The authors investigated to what extent conviction of a violent crime, suicide and premature death were specific to schizophrenia and related disorders.
Findings: Over the 38-year study period, male patients were 7.5 times more likely and female patients 11.1 times more likely to suffer the three adverse outcomes than control subjects matched by age and sex from the general population. The analysis of nearly 25,000 individuals with schizophrenia and related disorders found that 13.9% of the men and 4.7% of the women were convicted of a violent offence, died from suicide or died from other causes within the first five years following diagnosis. Substance abuse disorders, previous criminal conviction and a history of self-harm increased risk further
The authors noted that, while Sweden's incarceration rate is low compared to other countries, the prevalence of psychiatric and substance abuse disorders is "largely similar to those in the USA and other high-income countries." Unlike the Swedes, the United States systematically overlooks the role of mental illness in a host of social and health conditions. Whether the Swedish findings would be replicated in the US will remain unknown until we begin collecting similar statistics.

Doris A. Fuller
Chief of Research and Public Affairs
References:
- Fazel, S., Zetterqvist, J., Larsson, H., Langstrom, N., Lichtenstein, P. "Antipsychotics, mood stabilisers, and risk of violent crime." (7 May 2014). The Lancet.
- Fazel, S., Wolf, A., Chang, Z., Larsson, H., Goodwin, G.M., Lichtenstein, P. (March 2015). "Depression and violence: A Swedish population study." The Lancet Psychiatry.
- Fazel, S., Wolf, A., Palm, C., Lichtenstein, P. (June 2014). "Violent crime, suicide, and premature mortality in patients with schizophrenia and related disorders: a 38-year total population study in Sweden." The Lancet Psychiatry.
Next week: Research Weekly will report daily from the 5th Biennial Schizophrenia International Research Society Conference
Research Weekly is a summary published as a public service of the Treatment Advocacy Center and does not necessarily reflect the findings or positions of the organization or its staff. Full access to research summarized may require a fee or paid subscription to the publications.
To comment, visit our Facebook page.
Visit our blog archive to read all our recent posts.
10 WAYS WOMEN WITH SEVERE MENTAL ILLNESS SUFFER MORE
Women with a psychiatric disease are more likely to be arrested, incarcerated, victimized or suicidal, according to a review of research from the Treatment Advocacy Center
Women with severe mental illness suffer more consequences than men with the same conditions and women without a psychiatric disease, according to a comprehensive review of evidence from the Treatment Advocacy Center.
"10 Ways Women with SMI are Overrepresented, Underserved" shows that women with a psychiatric disease - typically untreated -- are more likely to be arrested, incarcerated, victimized or suicidal, and to suffer from multiple medical conditions or substance abuse, the review found.
"We already know that people with psychiatric disorders are vulnerable to a host of ills," said Treatment Advocacy Center Executive Director John Snook. "But for women, the consequences are even more severe."
The statistics paint a stark picture, with severe mental illness disproportionately impacting women.
Among the key findings:
- Women with a psychiatric disease are almost twice as likely to be victimized - to have been beaten, sexually assaulted or otherwise abused;
- Women with severe mental illness are twice as prevalent as men in state prison populations;
- Women with schizophrenia are less likely to be admitted to the hospital and, once admitted, they are hospitalized for fewer days than their male counterparts.
"The consequences suffered by women with severe mental illness are still more evidence that our mental health is broken and grossly insufficient, leaving patients and caregivers to fend for themselves," Snook said.
Read the full review here.
The Treatment Advocacy Center urges lawmakers take the following actions to reduce negative outcomes and social costs associated with the consequences of untreated severe mental illness:
- Fund and promote research and data collection to determine the unique role of gender in the consequences of severe mental illness. Women represent half of the population and are overrepresented in a host of consequences from severe mental illness. Determining the best way to address this problem requires rigorous data collection and analysis to identify gaps in the treatment system, access issues and underlying causes and barriers that contribute to women disproportionately experiencing negative outcomes.
- Fix the broken mental health system by passing federal mental health reform legislation that helps people with severe mental illness. Several important proposals are currently moving through Congress, including the Helping Families in Mental Health Crisis Act (HR 2646), the Mental Health Reform Act (S 1945) and the Mental Health and Safe Communities Act (S 2002). These proposals contain a broad range of solutions to address the shortage of psychiatric beds in community hospitals, decriminalize mental illness, fund evidence-based practices to help people with severe mental illness and expand the mental-health workforce.
There Has Been More Than One Death Behind Bars
(Mar. 24, 2016) A number of advocates across Virginia are calling for a federal investigation into the death of Jamycheal Mitchell – a mentally ill man who died of starvation in a Virginia jail last August while waiting for a hospital bed to open up in a mental health facility (“Advocates call for federal investigation of death of Va. Man jailed for stealing junk food,” Richmond Times-Dispatch, Mar. 23).
 Like an increasing number of the mentally ill, Mitchell sat in the Hampton Roads regional jail in Portsmouth, Virginia for months as he waited for a bed to open up. While incarcerated, Mitchell dropped over 34 pounds in just three months. Then, on August 19, 2015, Mitchell’s severely emaciated body was found unresponsive on the floor of his cell. He had starved to death while in jail custody.
Why didn’t Mitchell get a bed after a judge ordered him to treatment? A recent report shows that an “overwhelmed” state employee placed the order in a desk drawer when she received the fax instead of adding Mitchell to the waiting list. The drawer contained a “significant number of (competency restoration orders that had not been entered,” according to the report.
In a statement, the NAACP of Portsmouth called Mitchell’s death “one of the biggest civil and human rights violations of our time.”
“The events surrounding the death of Jamycheal Mitchell in the Hampton Roads Regional Jail are beyond disturbing and inhumane in nature,” said James P. Boyd, president of the NAACP Portsmouth chapter. “We intend to seek an independent federal investigation to ensure accountability and improvements are executed.”
We applaud advocates for calling for a federal investigation into this tragic death. But Jamycheal isn’t the only person with severe mental illness who has died behind bars recently.
Natasha McKenna was arrested early last year on a charge of assaulting a police officer while suffering a psychotic break due to untreated severe mental illness. She was taken to the Fairfax County jail in Virginia and had been there a week before she was shocked four times with a Taser during an altercation with jail deputies. McKenna died four days later.
Diagnosed with bipolar disorder, Keaton Farris, 25, was passed through four jails while awaiting a bed at the overburdened Washington state psychiatric hospital. Farris died of dehydration and malnutrition while behind bars last April.
An inmate with mental illness at the Santa Clara County Jail in California, 31-year-old Michael James Tyree died in late August at the hands of three correctional officers. According to reports, the three deputies entered Tyree's single-person cell and viciously beat him. The county medical examiner-coroner said Tyree died of internal bleeding from multiple blunt force injuries.
What these tragedies all boil down to is an overwhelming failure of our mental health system.
We need to shine the national spotlight on each of these deaths.
To comment, visit our Facebook page.
Visit our blog archive to read all our recent posts.
Help Others Help the Mentally Ill Receive Treatment – guest commentary
(Mar. 23, 2016) Nuts. Crazy. Lunatic. Maniac. Psychopath. Wacko. These are words I frequently hear used to describe people suffering from mental illness.
 Would we refer so callously to people with cancer, muscular dystrophy or Parkinson’s disease?
Mentally ill individuals have a disease, not a character flaw. Mental illness is not something people choose.
Approximately 10 million Americans struggle with serious mental illness, but millions are going without treatment as families struggle to find care for their loved ones. As with any other serious illness, people suffering from mental illness need medical treatment. Therein lies the problem.
State laws vary, but all states set strict controls on involuntary hospitalization, limiting it to circumstances when a person is an imminent danger to self or others, or likely to become so. These laws give people with severe mental illness the right to decide when, where, how or even if they will receive treatment.
Families must watch their loved ones descend, sometimes slowly, into Code Red territory because current laws do not allow them to push the “help” button until the person reaches the crisis stage. Only when an ill person becomes a danger, as determined by a judge at a commitment hearing, can they be involuntarily hospitalized and treated.
But by this time, it is sometimes too late.
Our failure to care for the mentally ill comes at a high cost. Yet with proper diagnosis and treatment, many patients are able to overcome mental illness, contribute to society and live normal and happy lives.
Last November, the Helping Families in Mental Health Crisis Act (HR 2646) legislation introduced by U.S. Reps. Tim Murphy and Eddie Bernice Johnson advanced out of the House Energy and Commerce Health Subcommittee. The bill currently has the strong bipartisan support of 185 cosponsors.
The Helping Families in Mental Health Crisis Act would revamp our mental health system and ensure that people suffering from severe mental illness receive the care they need. It would increase the number of inpatient psychiatric beds, authorize court-ordered assisted outpatient treatment for individuals with a long history and pattern of proving a danger to themselves or others, and make adjustments to HIPAA privacy laws by helping patients get treatment for their illness before they reach the violent breaking point.
I lost an adult son to suicide. He suffered from untreated bipolar disorder. Although too late to save my son, HR 2646 would save the lives of others struggling from untreated mental illness by enabling them to receive treatment sooner, making them less likely to reach a violent breaking point.
DOTTIE PACHARIS
FORT MYERS, FLORIDA
Read the entire column here.
To comment, visit our Facebook page.
Visit our blog archive to read all our recent posts.
RESEARCH WEEKLY: Risks, Rewards and Long–term Antipsychotics
(Mar. 22, 2016) Given the stakes involved with antipsychotic medication - the side effects that can result either from taking or not taking them for psychotic conditions can be life-changing - it should come as no surprise that they are a recurring source of controversy in the mental health community.
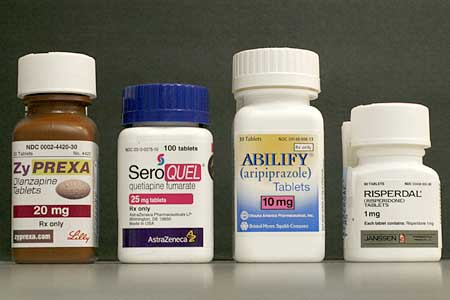 Two psychiatrists with long careers in treating psychotic disorders have recently analyzed the literature and controversies around the long-term use of antipsychotics, in light of criticiism that antipsychotics worsen psychosis and the clinical outcomes in schizophrenia.
Ronald W. Pies, MD, professor of psychiatry at SUNY Upstate Medical and Tufts universities, comments on recent studies and their interpretations in "Long-term antipsychotic treatment: Effective and often necessary, with caveats" in Psychiatry Times. Allen Frances, professor emeritus and former chair of the department of psychiatry at Duke University School of Medicine and chair of the DSM-IV task force, examines the topic in Psychology Today and mass media.
Here is a brief summary of what the authors say. Links to complete versions are provided in the references below.
What the Literature Says
"It is important to understand that only a portion of people with a first psychotic episode have schizophrenia, which is usually a very chronic illness," Pies writes in Psychiatry Times. "Many have quite brief bouts of psychosis that never return, making long-term antipsychotic treatment unnecessary." He suggests that some confusion about long-term antipsychotics usage results when this population is inappropriately conflated with the population living with chronic psychotic disorders.
According to Pies's review of related psychiatric literature, "There is no convincing evidence that maintenance treatment causes worsening of schizophrenia or related psychotic illnesses, or leads to poorer outcomes, when compared with discontinuation of the antipsychotic." To the contrary, he says, "the preponderance of evidence points to the net benefits of long-term (antipsychotic) use in patients with schizophrenia," including lower overall mortality.
"We need to make modest claims - not sweeping generalizations - about the literature on long-term use of antipsychotic medication," says Pies. "Indeed, these medications are almost certainly over-used - without substantial evidence for their efficacy - in patients with ordinary anxiety disorders or insomnia; for adolescent 'acting out'; and for 'agitation' in geriatric or nursing home populations."
That said, Pies continues, while "'gold-standard,' randomized, placebo-controlled studies are fewer than we would like" and subject to different interpretations, "most randomized, long-term studies of schizophrenia support the net benefit of antipsychotics in preventing relapse of the illness. Some data also show better 'quality of life' with maintenance antipsychotic treatment, compared with drug discontinuation."
Risks vs Benefits
In the end, Pies says, "Discussion of long-term (antipsychotic) use must be placed in the larger perspective of general medical care, in which physicians are constantly struggling with the perennial 'risk vs. benefit' equation. Many life-saving treatments in other medical specialties - from cancer chemotherapy to cardiac surgery - are associated with significant risks. But we must also consider the risks of absent or inadequate treatment, and the inherent morbidity and mortality of the illness itself."
Pies's reader-friendly analysis of the literature examining long-term antipsychotic use is available online in its entirety from Psychiatry Times.
Psychiatrist Allen Frances of Duke University describes his own research and clinical experience with long-term antipsychotic medications and quotes from an interview with Pies in "Setting the record straight on antipsychotics," published in Psychology Today, where he authors the column Saving Normal. "The misleading idea that antipsychotic medications cause or worsen psychosis legitimizes the incorrect view that long-term medication is bad for everyone," Frances concludes. "A minority of people with chronic, severely impairing psychotic symptoms may eventually do fine off meds, but the majority will have relapses that are always disruptive and often dangerous."
Frances offers further analysis of the antipsychotic controversy in a Huffington Post blog, "Do antipsychotics help or harm psychotic symptoms?"
The Treatment Advocacy Center has long decried the overuse and misuse of psychotropic medications, especially for off-label applications and children. At the same time, the preponderance of evidence continues to document the usefulness of antipsychotic medications in saving and improving the lives of at-risk individuals with severe and persistent psychotic disorders.
Doris A. Fuller
Chief of Research and Public Affairs
References:
Research Weekly is a summary published as a public service of the Treatment Advocacy Center and does not necessarily reflect the findings or positions of the organization or its staff. Full access to research summarized may require a fee or paid subscription to the publications.
To comment, visit our Facebook page.
Visit our blog archive to read all our recent posts.
Texas Man Condemned to Death Despite Lifelong, Severe Mental Illness
(Mar. 21, 2016) Adam Ward is scheduled to be executed in Texas Tuesday for the 2005 murder of a code enforcement officer in the city of Commerce (“Texas set to execute man amidst claims of ‘severe mental illness’,” Buzzfeed News, Mar. 21).
 Ward – a 33-year-old diagnosed with severe bipolar disorder – fatally shot Michael “Pee Wee” Walker in June 2005 as the officer was documenting code violations because of junk piled inside and outside of Ward’s home. Ward ran out of the house and opened fire on Walker. Walker died after sustaining nine gunshot wounds in total.
According to court documents, Ward confessed to killing Walker soon after the murder, saying he believed “the City” was out to get their family and that the “Illuminati” controlled the majority of the government. He also claimed that he shot Walker because he feared for his life, as Walker had threatened to call the cops.
Ward’s lawyers appealed to the U.S. Supreme Court last week, asking the court to stay his execution on the grounds that he is severely mentally ill and should be held to be constitutionally ineligible to be executed.
The appeal argues that Ward's act of murder was “inextricable from the delusions and paranoia fed by his disabling bipolar disorder” and that his mental illness, traced back to his early childhood, is “so severe, so well-documented, and so deeply present” in his life that it made him constitutionally ineligible for the death penalty.
“Adam’s lifelong struggle with bipolar disorder, combined with his isolation and toxic family life, finally culminated in tragedy when he shot and killed City of Commerce Code Enforcement Officer Michael Walker on June 13, 2005,” Ward’s appeal argues.
The state responded that Ward’s claims are without merit and that he had not presented any new evidence.
Ward would become the ninth person to be executed this year, and the fifth to be executed in Texas.
Ward is not the first, and likely not the last person with severe mental illness to commit a violent act that carries the death penalty.
It goes without saying that the lives lost in crimes committed by people in psychiatric crisis are tragedies. Nonetheless, executing mentally ill defendants who acted violently because their treatable brain diseases were not treated takes the criminalization of mental illness to the ultimate inhumane extreme.
To comment, visit our Facebook page.
Visit our blog archive to read all our recent posts.
Mentally Ill Man Responsible for Death of Maryland Police Officer Knew He Needed Help
(Mar. 17, 2016) Michael DeAndre Ford, 22, reportedly reached out for help before traveling to a police station in Prince George’s County, Maryland Sunday afternoon with a plan to commit suicide-by-cop (“Man arrested in police station gun battle described as troubled, mentally ill,” the Washington Post, Mar. 15).
 Hyacinth Tucker – a friend and former legal guardian of Ford – was busy the day Ford called and said he wanted to come by to talk.
Reflecting on the call now, Tucker said, “had I talked to him when he wanted to come by, maybe things would have been different.”
Instead, Ford drove to the Maryland police station and opened fire. An officer was killed and Ford was wounded.
Michael Ford struggled with severe mental illness and had minor run-ins with the law over the years, according to family and court records.
Shante Ramos, the brothers’ 30-year-old aunt, said Michael has bipolar disorder and reacts badly when he doesn’t take his medications. He was homeless at the time of the shooting.
“Michael definitely needed help,” Ramos said. “It’s breaking my heart.”
Michael Ford was officially charged with second-degree murder on Tuesday.
Why was this severely ill, young man allowed to decompensate untreated and unhoused on the streets?
Maryland is one of only four states that do not offer assisted outpatient treatment (AOT) – an evidence-based, life-saving program – to residents suffering with severe psychiatric disorders.
Ford needed help. The signs were there but the resources were not, in yet another preventable tragedy. How many more will it take before policy-and-lawmakers in Maryland take action?
To comment, visit our Facebook page.
Visit our blog archive to read all our recent posts.
“I Could Have Been James Holmes” – guest commentary
(Mar. 16, 2016) My name is Brock Miller. I am a 24-year-old white male, who grew up in a two-parent household in Colorado. I am currently a student at the University of Denver Sturm College of Law.
 I know most, if not all, of you reading this do not know who I am, but if things had gone differently for me over this past year, it is very possible you would know my name, for all the wrong reasons.
I started law school in August 2013 and I quickly got sucked into the trap of thinking that in order to be successful I needed to focus exclusively on school, and cut out all other parts of my life. By January 2015 my unbalanced lifestyle caught up to me and my mental health began to deteriorate. By March 2015, things had still gotten to the point I could no longer make it through a class or any other social situation without violently weeping. Additionally, I had begun to have unpredictable mood swings, and was hearing voices on occasion.
This is the part of my story where I want to pause and recognize that my life could have gone one of two ways. One possibility was I could have not received the care I needed, which could have led to: relationships around me falling apart, me taking my own life, or me becoming violent towards others. The other possibility was I could receive the care I needed in order to get control of my mental illness and I could go along living my life as I had before.
Fortunately for me, I was blessed with the resources, connections, and support system I needed to get into see a psychiatrist who prescribed the correct medications, and a psychologist who gave me the right strategies to recover. I had a wife who stuck by me every step of the way. I had an insurance plan that included mental health services, and I had money in the bank to pay co-pays and deductibles. But, what if my mental illness got to the point that I began having more extensive delusions and the voices began to speak to me more frequently?
These questions send a shiver down my spine and force me to acknowledge a frightening reality, which is that, if just a few things would have been different, I could have been James Holmes. When I have expressed this thought to some of my friends and family, they reply, “He was a monster, you aren’t. You wouldn’t have let it get to that point!” The thing that these people do not understand is there were times when I felt that I was not in control of my thoughts or actions. I suppose the best way to describe it is that I was not myself anymore. In short, it is my belief that if things had been slightly different, there is no way to predict what I would have done.
I am not attempting to downplay what happened to the victims in the theater that night, and I am certainly not advocating that those who have a mental health illness should be given some sort of immunity. I’m suggesting that universal access to quality mental health care would save lives.
We as a country need to remove the stigma associated with mental illness and start looking deeper into the amount of access those with mental illnesses have to quality mental health providers.
BROCK MILLER
DENVER, COLORADO
Read the entire column here.
To comment, visit our Facebook page.
Visit our blog archive to read all our recent posts.
RESEARCH WEEKLY: The Role of Asylum in Treatment
(Mar. 15, 2016) What does "asylum" mean in the context of mental illness treatment?
In popular usage, "asylum" has long been linked to state psychiatric hospitals, once known as "insane asylums." What asylum should mean, two authors maintain in a recent publication, is "sanctuary" - a place that provides "protection, safety, security and social support."
In "Rediscovering the concept of asylum for persons with serious mental illness," H. Richard Lamb, MD,* and Linda E. Weinberger, PhD, call for a recognition that many individuals with severe mental illness still need the functions state hospitals once performed in order to live optimally.
The Functions of Asylum
They identify five such functions:
- Lowering stress
- Providing protection and social support
- Matching demands for performance to capabilities
- Providing adequate treatment services
- Supplying structure
"Asylum can be provided in the home by the patient's family or in a community facility, such as a board-and-care home," the authors write in the Journal of the American Academy of Psychiatry and the Law. "In many cases, the structure of a psychiatric hospital is needed."
"Serious problems will most likely arise whenever a community lacks adequate equivalents for the full range of functions traditionally served by state mental hospitals. This includes the provision of asylum to those patients who need it. Indeed, it is apparent that many of the problems plaguing deinstitutionalization today derive, first, from our failure to recognize that some psychiatric patients with serious mental illness still have a need for asylum and, second, from our failure to offer that asylum even when we recognize the necessity."
Practical Realities
The authors describe four situations in which the concept of asylum has practical impacts:
- Rehabilitation. Effective rehabilitation can reduce the need for asylum but, for individuals in need of shelter or structure, "the elements of asylum often need to be supplied concurrently if rehabilitation programs are to achieve maximum results."
- Expectations. There is "a narrow line" between two dangers in treatment - too much and too little stimulation - and it needs to be walked with a recognition that "fruitless efforts to push people to adjust to a lifestyle beyond their capabilities" causes the patients anguish and runs the risk of contributing to their relapse.
- Institutionalism. This syndrome of withdrawal, disinterest and excessive reliance on other institutions was once thought to be entirely the result of living in institutions providing asylum. Increasingly, institutionalism is viewed at least in part as a reflection of the schizophrenic disease process. "A place of asylum should include treatment interventions that increase the individual's ability to tolerate stress. Testing these interventions in a safe and supportive environment can assist in assuring successful transition to less structured settings in the community."
- Incarceration. Mentally ill offenders have additional needs for the functions of asylum when they are released from jails and prisons. Offenders without access to such functions are at higher risk for reoffending and relapse.
"Treating persons with serious mental illness requires more than just making the correct diagnosis, prescribing the right medications and providing the appropriate psychotherapeutic approach," Lamb and Weinberger conclude. "There should be an in-depth understanding of patients' needs for structure and their ability to cope with stress, as well as an assurance that they are in suitable living situations. Above all, the importance of asylum and sanctuary cannot be underestimated."
* H. Richard Lamb is a member of the Treatment Advocacy Center Board of Directors
Doris A. Fuller
Chief of Research and Public Affairs
References
Lamb, H. Richard, Weinberger, Linda E. (1 March 2016). (1 March 2016). Rediscovering the concept of asylum for persons with serious mental illness. Journal of the American Academy of Psychiatry and the Law.
Research Weekly is a summary published as a public service of the Treatment Advocacy Center and does not necessarily reflect the findings or positions of the organization or its staff. Full access to research summarized may require a fee or paid subscription to the publications.
To comment, visit our Facebook page.
Visit our blog archive to read all our recent posts.
|
|

