(Aug. 31, 2016) If a "miracle drug" that reliably reduced life-threatening symptoms of heart disease and lowered treatment costs were prescribed to only 4% of the cardiac patients who would benefit from it, the official and public reaction likely would be strong and negative.
Yet this continues to be the status of the antipsychotic medication clozapine, often known by its trade name, Clozaril, more than 25 years after the drug's 1990 introduction in the United States.
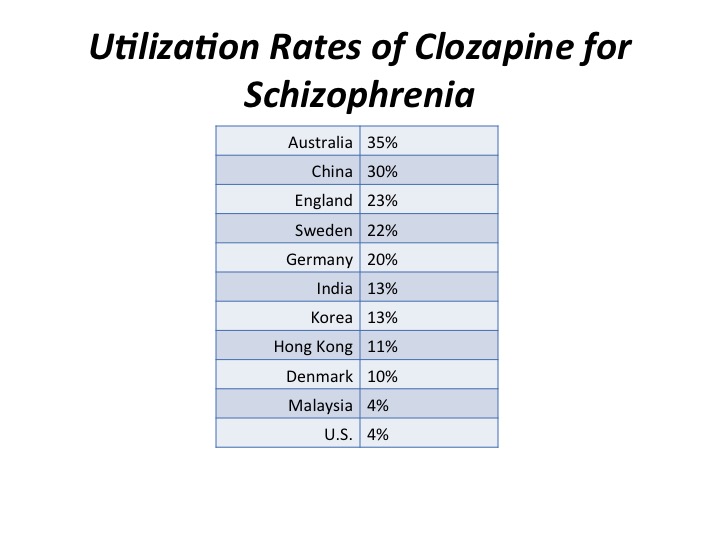
A new analysis of international clozapine utilization rates conducted for the Treatment Advocacy Center found use in the United States of the medication tied with Malaysia's at 4% of schizophrenia patients. E. Fuller Torrey, MD, author of a 2015 survey of comparative use of clozapine among the states, analyzed usage rates in 11 nations on four continents to develop the relative rankings.
At the same time, a study of the business case for using clozapine reports that prescribing clozapine to all the treatment-resistant patients with schizophrenia served by the Veterans Health Administration (VHA) would save the US government nearly $300 million annually, despite the cost of monitoring for side effects.
 International Comparison
Clozapine today remains the only antipsychotic medication approved by the Food and Drug Administration (FDA) for treatment-resistant schizophrenia. A recent study reports that as many as one-third of individuals with schizophrenia are treatment-refractory, meaning they experience persistent psychosis despite adequate treatment with other medications.
Because of side effects on the white blood cells that occur in 8 out of every 1,000 clozapine users, individuals taking clozapine undergo weekly blood tests for the first six months of use, then less often, to identify those for whom the clozapine must be stopped. If the blood is not monitored the side effect could ultimately be fatal. The testing requirement is often cited as a reason for the drug's underuse.
In other nations, however, the testing does not erect the same barrier to treatment of psychotic conditions. Australia makes the most widespread use of clozapine, with 35% of schizophrenia patients receiving the drug. In England, nearly six times more schizophrenia patients receive clozapine than in the United States; in South Korea, more than four times as many patients do.
Use across the United States is also uneven. The Treatment Advocacy Center's Clozapine for treating schizophrenia: A comparison of the states found a seven-fold variation. Based on Medicaid and pharmacy data, South Dakota made the most widespread use of the drug, with 15.6% of schizophrenia patients receiving Medicaid taking the drug, compared with Louisiana, Nevada and Oregon, where only 2% of candidates for the medication were taking it. Only six states achieved the 10% penetration rate considered to be a bare minimum.
"Unconscionable" Practice
The care of schizophrenia patients "represents a major public health challenge in human and economic terms," according to a recent editorial in JAMA Psychiatry, which termed longstanding resistance to prescribing the drug "unconscionable." Direct and indirect costs of schizophrenia for 2013 are estimated at $155 billion in the United States - $44,773 per individual with the disease - in a recent study.
Clozapine is also the only drug with FDA approval for reducing suicidal behavior, which kills more than 40,000 people a year in this country. The medication additionally has been reported to reduce mortality risk for people with serious mental illnesses including schizophrenia. Richard Hayes and colleagues in 2014 reported clozapine associated with lower risk of death from all causes and specifically from suicide, compared to other antipsychotic drugs. The authors found no evidence that the lower risk of death resulted from the mandatory clinical monitoring.
Jessica L. Goren and colleagues in June 2016 reported that the VHA would save $22,444 per veteran with treatment-resistant clozapine over the first year of therapy, primarily from reduced hospitalization.

Doris A. Fuller
Chief of Research and Public Affairs
References:
Next Week: Clozapine by the Numbers
Research Weekly is a summary published as a public service of the Treatment Advocacy Center and does not necessarily reflect the findings or positions of the organization or its staff. Full access to research summarized may require a fee or paid subscription to the publications.
To comment, visit our Facebook page.
Visit our blog archive to read all our recent posts.


 (Oct. 4, 2016) Critics of psychiatry who argue that people with schizophrenia would be better off without antipsychotic medication misrepresent the best available evidence, including research on medication and quality of life
 In any given year, fewer than half the estimated 8.1 million of people with these psychiatric disorders in the United States receive treatment. Count among the many barriers to their treatment an acute and worsening shortage of psychiatrists, as a new report in Health Affairs details.